Start your free 3-day trial — no credit card required, full access included

Aortoiliac TEA in bilateral peripheral arterial occlusive disease stage IIb

Reading time readingtime 29:44 min.
Activate now
  1. Suturing the aortotomy

    Suturing the aortotomy
    Soundsettings

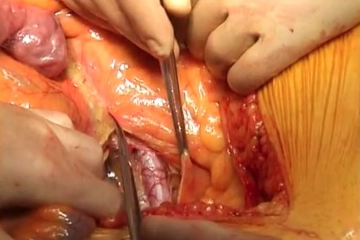
    The aortotomy is closed with a continuous direct suture (monofilament, 4/0 or 5/0 depending on the thickness of the aortic wall). Flush through a residual gap in the aortic suture, checking central inflow and peripheral backflow. After completing the suture, gradually release the blood flow under digital compression control. Antagonise the heparin and remove all bulldog clamps still in situ.

    Tips:

    1. Direct suturing of the aorta is the biologically superior alternative compared with synthetic patches, as patch plasty is prone to aneurysm formation in the long term, necessitating repeat procedures. However, direct suturing requires the aorta to have a diameter of 16 mm or more. With a diameter of 14 mm or less, insertion of a synthetic patch is required. This is also necessary when an incision extending into the common iliac artery is indicated.

    2. Bowel perfusion should be checked once the blood flow has been restored.

    3. As the colour of the sigmoid colon at this stage of the procedure does not reveal anything about the quality of perfusion, the marginal arteries can be checked with a Doppler device if there is any doubt about the sigmoid perfusion.
  2. Closing the retroperitoneum

    Closing the retroperitoneum
    Soundsettings

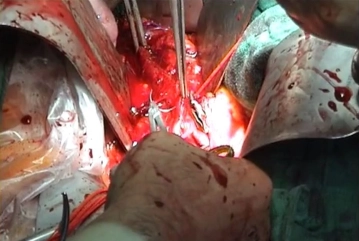
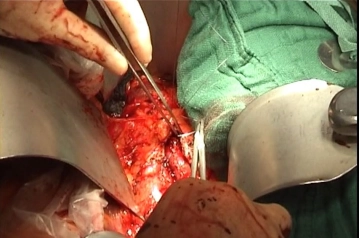
    First, close the retroperitoneal lymphatic and adipose tissue pad anterior to the aorta with a running suture. Follow this with a second layer of a running suture closing the retroperitoneal cover. This does not anchor the flexura duodenojejunalis, but rather repositions it anteriorly and allows it to move freely in response to peristaltic waves.

    Then close the abdominal wall in layers and check peripheral perfusion (leg pulses, capillary refill); these two steps are not shown here.

    Tips:

    1. Retroperitoneal closure is particularly decisive for long-term outcome. Insidious paraaortic infections, which may lead to aortoduodenal fistulae, occur above all when the flexura duodenojejunalis has been firmly anchored to the graft bed. This is prevented by the two-layered, staggered closure of the retroperitoneum.

    2. A retroperitoneal Redon drain for 24 hours may be useful as it may signal acute bleeding (however, a dry drain does not reliably rule out bleeding). A larger retroperitoneal haematoma may also inhibit the onset of peristalsis and healing in the graft bed.

    3. Never forego retroperitoneal tissue coverage of the graft bed under any circumstances! If the tissue to be sutured is fragile, it may be better to preplace interrupted sutures and then tie them successively. If that does not work either, coverage with a right- or left-pedicled greater omentum flap may be required.

  3. Laparotomy

    Laparotomy
    Soundsettings

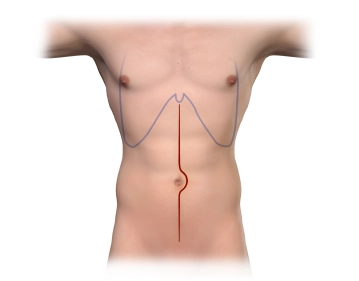
    Perform median laparotomy from the xiphoid down to the symphysis, carrying the incision to the left of the umbilicus.

    Tips:

    1. Maintain adequate distance from the umbilicus and do not incise the skin tangentially as this runs the risk of wound edge necrosis.

    2. If the incision damages the cartilage of the xiphoid, it may lead to the development of a so-called scar ossification. The incision should therefore begin somewhat lateral to the xiphoid.

  4. Opening the retroperitoneum and exposing the left renal vein

    Opening the retroperitoneum and exposing the left renal vein
    Soundsettings

    Open the retroperitoneum, sparing the inferior mesenteric artery (IMA), somewhat to the right lateral over the palpable aorta and the right iliac axis. After sweeping the small bowel loops to the right, coagulate any visible small vessels step by step and in advance to reduce unnecessary bleeding. After mobilising the duodenojejunal flexure, locate the crossing left renal vein as the upper boundary.

Eventration of the small bowel

Eventrate the small bowel to the right. For this purpose, tilt the operating table about 30° to the

Activate now and continue learning straight away.

Single Access

Activation of this course for 3 days.

US$9.27 inclusive VAT
Add to cart

Most popular offer

webop - Savings Flex

Combine our learning modules flexibly and save up to 50%.

from US$4.30 / module

US$51.61/ yearly payment

price overview

vascular surgery

Unlock all courses in this module.

US$8.60 / month

US$103.23 / yearly payment

Add to cart
to top