Start your free 3-day trial — no credit card required, full access included

Aortofemoral bifurcation bypass (Y-graft) in peripheral arterial occlusive disease stage IIb-III

Reading time readingtime 33:34 min.
Activate now
  1. Exposing the right groin and femoral bifurcation

    Exposing the right groin and femoral bifurcation
    Soundsettings

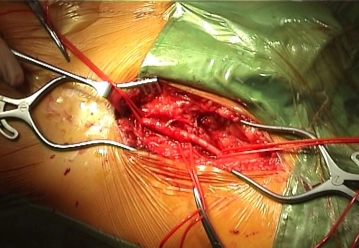
    Longitudinal skin incision about 1 cm lateral to the femoral artery and division of the subcutis with painstaking haemostasis. While sparing the lymphatics, divide the lateral lymphatic collectors immediately caudal to the groin between clamps and secure the ends with suture ligatures. Dissect and loop the common femoral artery, superficial femoral artery and deep femoral artery. Assess the vessel wall (quality, calcification) by palpation.

    Tips:

    1. The first step is to expose the groin so that the abdominal cavity remains open only as briefly as possible. As a result, the patient cools down less quickly, which improves the postoperative phase and allows for faster extubation.

    2. Lateral access to the femoral artery allows staggered closure of the groin. This better secures the vascular reconstruction, and superficial wound healing disorders, such as wound margin necrosis, do not necessarily result in deep infection.

    3. Especially in PAOD Fontaine stage IV, the lymphatics and lymph nodes are often quite enlarged and represent a potential source of infection for the vascular reconstruction. Careful instrument dissection and no crude manipulation of the tissues within the wound with the fingers is therefore imperative!

    4. The medial circumflex femoral artery is located posteromediad (femoral artery -> deep femoral artery -> medial circumflex femoral artery). Its location and caliber vary greatly, and it often presents with a large caliber. It must be looped separately and clamped later, since injuries to this vessel can result in bleeding that is hard to manage.

    5. In PAOD Fontaine stage IV and during repeat procedures, pronounced adhesions between the femoral artery and the deep femoral vein are usually present. In these cases, time-consuming dissection is to be expected.
  2. TEA of the right femoral artery

    TEA of the right femoral artery
    Soundsettings

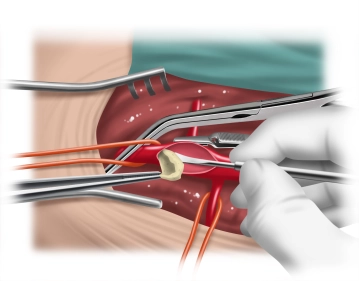
    After cross-clamping and longitudinal incision of the femoral bifurcation instill 2000 IU of heparinized saline upstream into the femoral artery and downstream into the superficial and deep femoral arteries. Identify a suitable dissection level and perform the local TEA.

    After inserting a moist gauze dressing (secured with a clip) and covering the groin wound with a moist abdominal towel, repeat the same procedure on the left groin (not illustrated).

    Tips:

    1. Do not force peripheral dissection.

    2. Ensure adequate exposure distad until a soft segment of the artery is reached.

    3. If necessary, secure with sutures any plaque that does not taper off peripherally.

    4. Plan for a possible profundaplasty, which requires exposure to the 3rd division of the vessel.

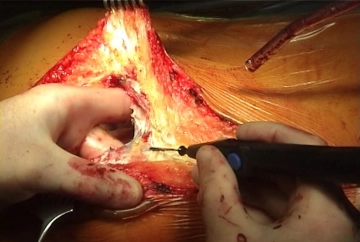
    5. If the TEA of the inguinal vessels results in a thin and fragile vascular wall, and the vascular suture cuts through easily, the situation can be saved by a trick. For this purpose, dissect a strip of fascia from the muscles of the upper thigh, apply it against the outside of the vessel and use it as a pledget to reinforce the suture of the vessel wall. In this case the stitches pass through both vessel wall and fascial pledget. From the outset this will stop not only any stitches from cutting through but also repair a vessel wall that has already been torn.

  3. Laparotomy

    Laparotomy
    Soundsettings

    Perform the median laparotomy from the xiphoid down to the symphysis, staying to the left of the navel.

    Tips:

    1. Maintain adequate distance from the navel and do not incise the skin tangentially, as this may result in wound edge necrosis.

    2. If the incision injures the xiphoid cartilage, this could trigger heterotopic ossification of the scar. The incision should therefore start slightly lateral to the xiphoid.

  4. Opening the retroperitoneum and exposing the aorta

    Opening the retroperitoneum and exposing the aorta
    Soundsettings

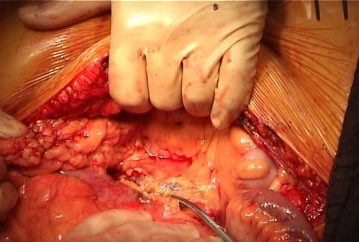
    After exploring the abdomen, push the transverse colon into the upper abdomen and eventrate the small intestine. Open the retroperitoneum slightly lateral to the right of and anterior to the palpable aorta and right iliac axis while protecting the inferior mesenteric artery (IMA).

    By blunt digital dissection, prepare the tunnels for pulling the limbs of the graft through later. On the right, the finger of the left hand stays lateral to the inferior vena cava on the iliopsoas muscle, on the left on the back of the iliac artery. On both sides, tunnel posterior to the ureter (incorrectly placed graft limbs may result in ureteral stenosis). From the groins, the finger of the right hand tunnels posterior to the respective inguinal ligament. The tunnelling fingers of both hands should touch in the retroperitoneum.

    Tips:

    1. The more marked the stenoses of the aorta and iliac axis are, the more pronounced are the collaterals in the retroperitoneum, which cause bleeding when severed and should be stopped immediately.

    2. Expose the aorta up to the traversing left renal vein, because in most cases a segment suitable for cross-clamping will only be found there.

Cross-clamping the terminal aorta

Loop the AMI and administer 5000 IU of heparin systemically. Cross-clamp the aorta inferior to the

Activate now and continue learning straight away.

Single Access

Activation of this course for 3 days.

US$8.92 inclusive VAT
Add to cart

Most popular offer

webop - Savings Flex

Combine our learning modules flexibly and save up to 50%.

from US$4.14 / module

US$49.69/ yearly payment

price overview

vascular surgery

Unlock all courses in this module.

US$8.28 / month

US$99.38 / yearly payment

Add to cart
to top