Start your free 3-day trial — no credit card required, full access included

Perioperative management - Robot-assisted right adrenalectomy

  1. Contraindications

    General contraindications

    The general contraindications to a robotic approach are based on the general contraindications to a minimally invasive approach. These include:

    · Contraindications to the creation of a pneumoperitoneum, e.g.

    o due to severe systemic disease,

    o or a manifest ileus with massive bowel distension

    o all clinical situations involving an abdominal compartment syndrome

    o extensive intra-abdominal adhesions (hostile abdomen)

    In addition, relative contraindications should be considered, in which preoperative optimisation may be possible, such as:

    · Severe coagulation disorders (Quick value < 50%, PTT > 60 sec., platelets < 50/nl),

    · marked portal hypertension with caput medusae


    Specific contraindications

    • No adrenalectomy without prior assessment of hormonal activity!
    • Extensive adhesions following previous operations
      Note: A retroperitoneoscopic approach may be useful here.
    • Due to the very low risk of malignancy, surgery is generally not indicated for hormonally inactive tumours < 4 cm with no suspicion of malignancy. Should surgery nevertheless be performed, this must be justified.
    • primary open approach for large malignant tumours with infiltration of surrounding structures or proven lymph node metastases
    • In bilateral primary hyperaldosteronism (idiopathic adrenal hyperplasia) without lateralisation: initiation of therapy with aldosterone antagonists.
    • No adrenalectomy but rather parenchyma-sparing adrenal resection (to preserve function, one third of an adrenal gland should be left in place).

      • In hereditary (bilateral) phaeochromocytomas, as the likelihood of a metachronous contralateral phaeochromocytoma is high and the risk of malignancy is considered low.
      • Cushing's syndrome caused by bilateral macronodular hyperplasia. A balancing act between cortisol control and residual hormonal function. Following a total adrenalectomy there is an obligatory need for substitution, with the risk of a life-threatening Addisonian crisis (acute adrenal insufficiency).
    • Myelolipomas and adrenal cysts should only be removed in the presence of clinical symptoms.
    • The further contraindications depend on the underlying conditions (operative risk) and on the significance of the adrenalectomy for the patient's quality of life or life expectancy.
  2. Preoperative diagnostic work-up

    Preoperative diagnostic work-up

    Adrenal tumours encompass a broad spectrum of benign and malignant changes that may affect both the morphology and the hormonal function of the adrenal gland. The aim of the diagnostic work-up is the precise classification of morphological and functional changes, in order to enable a sound therapeutic decision.

    The diagnostic work-up is based on a combination of clinical evaluation, endocrinological laboratory diagnostics and imaging studies.

    Clinical examination

    The baseline diagnostic work-up comprises a careful history and physical examination. In particular, measurement of blood pressure and heart rate are obligatory components, since many adrenal tumours are associated with cardiovascular changes.

    In principle, every adrenal mass should be investigated for possible hormonal activity. This includes in particular:

    • Catecholamines
    • Aldosterone
    • Cortisol
    • Sex hormones and their precursors

    Key clinical symptoms

    The symptoms depend on the hormonal activity of the tumour:

    • Phaeochromocytoma:
      Severe or treatment-refractory hypertension, paroxysmal headaches, palpitations and autonomic symptoms
    • Cushing's syndrome (hypercortisolism):
      Central obesity, 'moon face', 'buffalo hump', striae rubrae, hirsutism and plethora

    Screening for primary hyperaldosteronism (PHA) should be performed in particular in cases of arterial hypertension or hypokalaemia.

    Laboratory diagnostics and hormonal work-up

    Hormonal diagnostics are a central component of the work-up of every adrenal tumour.

    Autonomous cortisol secretion

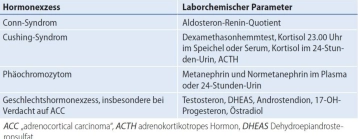
    The dexamethasone suppression test serves as the initial screening procedure when autonomous cortisol secretion is suspected.

    • Based on the suppressed serum cortisol, classification is made into:
      • non-functioning tumour
      • (possible) autonomous cortisol secretion
    • values > 5 ng/dl indicate confirmed autonomous cortisol secretion

    To confirm the diagnosis, a low or suppressed ACTH (< 10 pg/ml) is additionally required in order to exclude an ACTH-dependent cause (pituitary or ectopic).

    Phaeochromocytoma

    Diagnostics comprise the determination of:

    • metanephrines in plasma or
    • fractionated metanephrines in 24-hour urine collection

    In borderline findings, a clonidine suppression test can be performed.

    In addition, 3-methoxytyramine in plasma can serve as a marker for dopaminergic tumours and particularly when a SDHB mutation is suspected. This is especially relevant in tumours > 5 cm, as there is an increased risk of metastasis here.

    Primary hyperaldosteronism (Conn's syndrome)

    Primary hyperaldosteronism is characterised by autonomous, renin-independent aldosterone secretion.

    • Screening is performed using the aldosterone-to-renin ratio (ARR)
    • blood sampling standardised in the morning after 5–15 minutes of sitting

    In pathological screening, a confirmatory test is required, e.g.:

    • saline infusion test (2 l NaCl 0.9 % i.v. over 4 hours)
      • Healthy individuals: suppression of aldosterone
      • PHA: absence of suppression

    The influence of antihypertensive medication on the renin-angiotensin-aldosterone system (RAAS) must be taken into account in the interpretation.

    Sex hormone-producing tumours

    In case of clinical suspicion (e.g. hirsutism, gynaecomastia), tumour size > 4 cm or imaging suspicion of a carcinoma, the following parameters should be determined:

    • DHEA / DHEA-S
    • androstenedione
    • 17-α-hydroxyprogesterone
    • testosterone (in women)
    • 17β-oestradiol (in men and postmenopausal women)

    Note: Approximately 60–80 % of adrenocortical carcinomas are hormonally active, most frequently with production of cortisol and/or androgens.

    Human genetic diagnostics

    In patients with phaeochromocytoma, genetic testing is recommended regardless of age, tumour number or location according to current guidelines.

    Phaeochromocytoma is regarded as an indicator lesion for hereditary tumour syndromes:

    • approximately 12 % in unilateral tumours
    • up to 30 % in bilateral tumours, young patients or positive family history

    Imaging diagnostics

    Computed tomography (CT)

    CT is the primary imaging procedure for the assessment of adrenal tumours.

    It enables:

    • size determination
    • density analysis (Hounsfield units, HU)
    • assessment of infiltration and metastasis

    Non-contrast CT

    Non-contrast CT represents the first diagnostic step.

    • Lesions with < 10 HU are highly likely to be lipid-rich adenomas
      • sensitivity approximately 70 %
      • specificity approximately 95 %

    Contrast-enhanced CT

    In unclear findings, a supplementary contrast-enhanced examination is performed.

    • Assessment of the washout behaviour after 10–15 minutes
      • Adenomas: rapid washout
      • Malignant tumours: delayed washout

    Magnetic resonance imaging (MRI)

    MRI, in particular chemical shift imaging (in-phase/out-of-phase technique), serves for further characterisation.

    • Lipid-rich adenomas show signal loss in the out-of-phase sequence
    • Malignant tumours, metastases and phaeochromocytomas typically show no signal loss

    Staging

    For the detection of metastases, diagnostics should be supplemented by:

    • CT or MRI of the abdomen
    • CT of the thorax

    Nuclear medicine diagnostics

    MIBG scintigraphy

    MIBG scintigraphy is specific for phaeochromocytomas, but limited in SDHB mutations.

    Indications:

    • young patients
    • large tumours
    • suspicion of metastasis
    • multifocal or extra-adrenal tumours
    • hereditary syndromes

    In addition, it can be used for the planning of radionuclide therapy.

    PET/CT

    18F-FDG-PET/CT is the most important functional procedure in tumours suspected of malignancy.

    Indications:

    • unclear incidentalomas > 4 cm
    • suspicion of metastases
    • suspicion of adrenocortical carcinoma
    • SDHB-associated phaeochromocytomas

    It enables whole-body staging (with the exception of the brain, for which an MRI is required).

    When hereditary phaeochromocytomas are suspected, 18F-DOPA-PET/CT is particularly suitable due to its high specificity.

    Adrenal venous sampling (AVS)

    AVS serves for the functional lateralisation in primary hyperaldosteronism, in order to enable targeted surgical therapy and to avoid unnecessary adrenalectomies.

    In cases of unequivocal imaging localisation and particularly in young patients, AVS may be dispensed with in individual cases.

    Biopsy

    A needle biopsy of adrenal tumours is generally not recommended.

    Exceptions exist in:

    • suspicion of adrenal metastasis
    • known malignant underlying disease
    • unclear imaging

    Reasons against a biopsy:

    • lack of reliable differentiation between adenoma and carcinoma
    • risk of tumour cell dissemination

    Important: Before every biopsy, a phaeochromocytoma must be excluded biochemically, as otherwise life-threatening complications may occur.

    Summary

    The diagnostics of adrenal tumours require a structured approach combining clinical assessment, hormonal evaluation and modern imaging. The aim is the reliable differentiation between benign and malignant as well as hormonally active and hormonally inactive lesions, in order to enable adequate treatment planning.


    Diagnostics of adrenal tumours – overview

    1. Clinical and hormonal diagnostics

    Question

    Method

    Aim / interpretation

    Hormonal activity in general

    Baseline laboratory tests + clinical assessment

    Detection of functional tumours

    Hypercortisolism

    Dexamethasone suppression test

    > 5 ng/dl cortisol → autonomous secretion


    ACTH determination

    Low → ACTH-independent

    Phaeochromocytoma

    Plasma metanephrines or 24h urine

    Sensitive detection


    if necessary, clonidine test

    In borderline findings


    3-Methoxytyramine

    Indication of SDHB mutation

    Primary hyperaldosteronism

    Aldosterone-to-renin ratio

    Screening test


    Saline infusion test

    Confirmation

    Sex hormones

    DHEA-S, androgens, oestrogens

    Especially in clinical suspicion or tumour > 4 cm


    2. Imaging Diagnostics

    Procedure

    Finding

    Interpretation

    Non-contrast CT

    < 10 HU

    Probably adenoma


    > 20 HU

    Suspected malignancy

    Contrast-enhanced CT

    Rapid washout

    Benign lesion


    Delayed washout

    Malignant lesion

    MRI (chemical shift)

    Signal loss (out-of-phase)

    Lipid-rich adenoma


    No signal loss

    Malignancy / metastasis / PC

    CT thorax

    Search for metastases

    Component of staging


    3. Nuclear Medicine Diagnostics

    Procedure

    Indication

    Special feature

    MIBG scintigraphy

    Phaeochromocytoma

    Specific, but limited in SDHB

    FDG-PET/CT

    Suspected malignancy

    High sensitivity

    DOPA-PET/CT

    Hereditary PC

    High specificity


    4. Specialised Diagnostics

    Procedure

    Indication

    Aim

    AVS (adrenal venous sampling)

    Primary hyperaldosteronism

    Lateralisation

    Genetics

    Phaeochromocytoma

    Detection of hereditary syndromes

    Biopsy

    Rare individual cases

    Especially in suspected metastasis


    Diagnostic Algorithm for Adrenal Tumours

    Step 1: Incidental finding or clinical suspicion

    • Incidentaloma or symptomatic presentation
    • History + physical examination
    • Blood pressure, heart rate


    Step 2: Exclusion of hormonal activity (always mandatory!)

    Standard screening in all patients:

    • Dexamethasone suppression test → cortisol
    • Metanephrines → phaeochromocytoma
    • Aldosterone-to-renin ratio → in hypertension / hypokalaemia

    Extended diagnostics as required:

    • Sex hormones in clinical suspicion or tumour > 4 cm


    Step 3: Morphological characterisation

    Primary: CT (with/without contrast)

    • Determine size
    • Assess HU value
    • Infiltration / lymph nodes / metastases

    Supplementary: MRI

    • Unclear findings
    • Chemical shift for adenoma diagnostics


    Step 4: Estimate malignancy risk

    Indications of benignity:

    • < 10 HU
    • small tumour (< 4–6 cm)
    • homogeneous finding

    Indications of malignancy:

    · > 20 HU

    • Size > 4–6 cm
    • Inhomogeneity
    • Infiltration
    • Suspicious lymph nodes


    Step 5: Extended diagnostics as required

    • FDG-PET/CT → in suspected malignancy
    • DOPA-PET → in phaeochromocytoma
    • CT thorax → search for metastases
    • AVS → in PHA for lateralisation


    Step 6: Special cases

    • Phaeochromocytoma: always genetic testing
    • Biopsy: only in suspected metastasis and after exclusion of a PC


    Mnemonic

    “Every adrenal tumour needs two answers:”

    1. Is it hormonally active?
    2. Is it malignant or potentially malignant?

    → This forms the basis for the therapeutic decision.

  3. Preoperative preparation

    General

    General preoperative measures

    Irrespective of the tumour entity, the following aspects should be taken into account:

    • Optimisation of the cardiovascular situation
    • Correction of electrolyte disturbances
    • individual risk assessment
    • Planning of the operative approach (minimally invasive vs. open)

    Preoperative preparation on the ward

    • Breathing exercises: from the day of admission for pneumonia prophylaxis
    • Personal hygiene: shower the evening before (antiseptics)
    • Shaving: nipples down to and including the genitals
    • Premedication by anaesthesia
    • in the case of reduced general and nutritional status, additionally a high-calorie enteral nutrition solution (3 days preoperatively)
    • Thromboprophylaxis: (usually "Clexane 40"), anti-thrombosis stockings

    Caution: Preoperative review and adjustment of anticoagulant therapy:

    • Perioperative therapy with aspirin may be continued.
    • Clopidogrel (ADP inhibitor) should be discontinued at least 5 days before surgery.
    • Vitamin K antagonists should be discontinued for 7–10 days under INR monitoring.
    • DOACs (direct oral anticoagulants) should usually be discontinued 48 h preoperatively
    • Always after consultation with the treating cardiologist if necessary


    Bridging:

    • for vitamin K antagonists: bridging with short-acting heparins if INR outside the target range
    • For DOACs, bridging can usually be omitted owing to the short half-life. In the case of very high risk of occlusion/stroke: bridging under inpatient conditions with UFH and aPTT monitoring


    Preoperative preparation in theatre

    • Insertion of an indwelling catheter
    • Placement of an epidural catheter
    • Central venous catheter placement: usually during anesthesia induction.
    • Arterial line if required during induction
    • Perioperative antibiotics with e.g., Unacid


    Specific

    Preoperative preparation in adrenal tumours

    A structured preoperative preparation is essential in order to minimise perioperative complications. It is guided in particular by the hormonal activity of the tumour and should be carried out on an interdisciplinary basis.

    Interdisciplinary case discussion

    All patients with adrenal tumours should be presented preoperatively at an interdisciplinary tumour board.

    Those involved are usually:

    • Endocrinology
    • Visceral surgery / endocrine surgery
    • Radiology
    • Nuclear medicine
    • Oncology (in cases of suspected malignancy)

    The aim is to determine an individualised, guideline-compliant treatment strategy.

    α-blockade in phaeochromocytoma

    International and national guidelines recommend adequate preoperative α-adrenoceptor blockade prior to surgical resection of a phaeochromocytoma in order to reduce the risk of intraoperative hypertensive crises and cardiovascular complications.

    Preparation should generally be carried out over a period of at least 10–14 days.

    • Gold standard:
      Non-selective, irreversible α-blocker (e.g. phenoxybenzamine)
    • Mechanism of action:
      Irreversible, non-competitive blockade of α₁ and α₂ receptors
    • Aim of therapy
      • Blood pressure control
      • Avoidance of intraoperative catecholamine surges
      • Improvement of the intravascular volume status

    A common side effect is reflex tachycardia, caused by the α₂-receptor blockade. This can be treated if necessary by additional β-blockade. It is important here that β-blockade may only be initiated after sufficient α-blockade in order to avoid hypertensive crises.

    In addition, adequate volume substitution (e.g. increased salt intake) is recommended, as many patients are volume-depleted preoperatively.

    Current developments:
    The standardised approach with obligatory α-blockade is increasingly being discussed controversially. In selected cases, particularly in normotensive patients with small, biochemically mildly active tumours, an individualised approach without preoperative α-blockade may be considered. However, this should only be undertaken in experienced centres and after careful risk assessment.

    Perioperative glucocorticoid substitution in Cushing's syndrome

    In patients with florid Cushing's syndrome there is a high risk of postoperative adrenal insufficiency, as the contralateral adrenal gland is functionally suppressed by the chronic ACTH suppression.

    Therefore, peri- and postoperative glucocorticoid substitution is recommended.

    In addition, the following are often required preoperatively:

    • Optimisation of arterial hypertension
    • Control of diabetes mellitus
    • Correction of electrolyte disturbances
    • Treatment of infections
    • Thromboprophylaxis (increased thromboembolic risk)

    The aim is to achieve as stable a metabolic and cardiovascular situation as possible prior to the surgical procedure.

    Treatment of primary hyperaldosteronism

    In primary hyperaldosteronism (Conn's syndrome), the preoperative focus is on normalisation of the potassium level and control of the hypertension.

    • Medical therapy:
      • Aldosterone antagonists (e.g. spironolactone or eplerenone) for at least 2 weeks preoperatively
    • Potassium substitution:
      • often initially required until stabilisation

    The aim is to avoid perioperative cardiac arrhythmias and to optimise the circulatory status.

    Summary

    Preoperative preparation in adrenal tumours is crucial for perioperative safety and must be adapted to the respective hormonal activity. Whereas in phaeochromocytoma α-blockade is the priority, in Cushing's syndrome glucocorticoid substitution and metabolic stabilisation are essential. In primary hyperaldosteronism the focus is on normalisation of the potassium balance.

    Interdisciplinary planning is obligatory here.

  4. Informed consent

    Preoperative informed consent in adrenalectomy

    Preoperative informed consent comprises the explanation of general and specific operative risks. The individual risk depends on the patient's age, general condition and comorbidities as well as, in particular, on the hormonal activity of the tumour.

    General operative risks

    As with any surgical procedure, the following general risks exist:

    • Thromboembolic events (thrombosis, pulmonary embolism)
    • Infections (wound infection, intra-abdominal infections)
    • Bleeding and secondary haemorrhage, possibly requiring blood transfusion
    • Vascular and nerve injuries
    • Injury to adjacent organs
    • Conversion from a minimally invasive to an open procedure
    • Trocar hernias after a laparoscopic approach

    Specific procedure-related risks

    Due to the anatomical location of the adrenal gland, specific risks exist that may vary depending on the side and the operative approach:

    • Splenic injury, possibly requiring splenectomy (especially on the left side)
    • Injury to the left renal vein with potentially considerable bleeding
    • Injury to the tail of the pancreas with consecutive fistula or abscess formation
    • Injury to the diaphragm
    • Injury to the left colonic flexure
    • Gastric injury

    Endocrine and disease-specific risks

    The hormonal activity of the tumour substantially influences the perioperative risk:

    General hormonal risks

    • Acute hormonal dysregulation during or after surgery
    • Addisonian crisis (acute adrenal insufficiency), particularly after resection of hormonally active tumours

    Specific risks according to tumour entity

    Primary hyperaldosteronism (Conn's syndrome):

    • Persistence or incomplete normalisation of the arterial hypertension despite surgery

    Cushing's syndrome:

    • Increased risk of
      • Thromboembolism
      • Infections
    • Postoperative adrenal insufficiency requiring glucocorticoid replacement

    Phaeochromocytoma:

    • Risk of intraoperative hypertensive crises
    • Risk of local recurrence in case of tumour capsule opening due to tumour cell dissemination

    Special situations

    Bilateral adrenalectomy:

    • Need for lifelong replacement therapy with
      • glucocorticoids and
      • mineralocorticoids
    • Risk of developing Nelson's syndrome (ACTH-producing pituitary tumour)
      • Occurring in approximately 10–25 % of cases within about 10 years

    Summary

    In addition to the general surgical risks, the informed consent process prior to adrenalectomy particularly encompasses the specific anatomical and endocrine complications. The latter are closely linked to the underlying tumour entity and must be considered individually. Comprehensive patient counselling is crucial for perioperative management and the patient's informed consent.

  5. Anaesthesia

    Anaesthetic management in minimally invasive adrenal procedures requires careful planning, taking into account the hormonal activity of the tumour, the cardiovascular risks and the specific requirements of laparoscopic surgery.


    Anaesthetic technique

    • Performed under general anaesthesia with endotracheal intubation
    • Required because of:
      • controlled ventilation during pneumoperitoneum
      • intraoperative haemodynamic fluctuations
      • possibly prolonged operating time


    Analgesic techniques

    Adequate perioperative pain management is essential and is usually delivered multimodally.

    • Epidural anaesthesia (epidural catheter):
      • can be used for postoperative analgesia
      • particularly in cases of anticipated increased pain intensity or an open approach
    • Transversus abdominis plane block (TAP block):
      • regional anaesthetic technique for analgesia of the anterolateral abdominal wall
      • injection of a local anaesthetic between
        • M. obliquus internus and
        • M. transversus abdominis
      • alternative or possibly adjunct to the epidural catheter


    Vascular access and monitoring

    • Central venous catheter/two peripheral venous cannulae
    • Arterial line (invasive blood pressure monitoring):
      • indicated in:
        • cardiovascular risk factors
        • hormonally active tumours with haemodynamic instability (particularly phaeochromocytoma)
        • anticipated intraoperative blood pressure fluctuations
    • Invasive blood pressure measurement and a pulmonary artery catheter may be indicated in phaeochromocytomas and corresponding pre-existing cardiopulmonary conditions.


    Specific considerations according to tumour entity

    • Phaeochromocytoma:
      • pronounced haemodynamic fluctuations possible
      • close monitoring mandatory
      • extended haemodynamic monitoring may be required
    • Cushing's syndrome:
      • increased risk of thromboembolism and infection
      • perioperative glucocorticoid substitution required
    • Primary hyperaldosteronism:
      • attention to electrolyte disturbances (particularly hypokalaemia)


    Summary

    Anaesthetic care in minimally invasive adrenalectomy is based on general anaesthesia with controlled ventilation, supplemented by individually tailored pain management and risk-adapted monitoring.

    Particular attention is paid to hormonally active tumours, especially phaeochromocytoma, in which extended haemodynamic management may be required.

  6. Positioning

    For a transperitoneal approach, it is advisable to place the patient in a semi-lateral position.
    The patient, lying supine, is brought into a left semi-lateral position with the left arm extended out. For this, the right side of the body is padded underneath with an inflatable mattress. The right arm is extended out on a padded arm board. The legs and upper body are lowered and the entire table is brought into a 10–15 degree anti-Trendelenburg position.

OR-Setup

Basic arrangement in the roomPatient in left lateral position (right upper abdomen exposed uppermos

Activate now and continue learning straight away.

Single Access

Activation of this course for 3 days.

US$9.06 inclusive VAT
Add to cart

Most popular offer

webop - Savings Flex

Combine our learning modules flexibly and save up to 50%.

from US$4.20 / module

US$50.48/ yearly payment

price overview

robotics

Unlock all courses in this module.

US$8.41 / month

US$100.96 / yearly payment

Add to cart
to top